Read Next
International
Canada holds off on MAiD expansion for mental illness, targets people with dementia
Nancy Flanders
·

 Investigative·By Carole Novielli
BIAS: Is the Society for Maternal-Fetal Medicine pressuring parents to abort?
The Society for Maternal-Fetal Medicine (SMFM) recently issued a statement position claiming that "Abortion... is a core component of practice for MFM subspecialists nationwide," and says practitioners are "ethically obligated" to discuss the "economic implications of having a child with one or more health issues" with families facing prenatal diagnoses.
Should families trust this pro-abortion, biased organization of subspecialists? Is this really "reproductive justice"?

The Society for Maternal-Fetal Medicine (SMFM) recently issued a statement position revealing its heavy pro-abortion bias, which stated that abortion is a "core component" of being a maternal-fetal medicine doctor.
The statement, authored by individuals involved in and/or linked to the abortion industry, also indicated that anyone receiving a prenatal diagnosis should be informed of their abortion options; not only that, but the group recommends practitioners discuss with patients the potential "economic implications" of having a child with a disability.
The group advocated for earlier diagnosis of fetal anomalies through genetic screening and testing, which is notoriously unreliable, so that abortion can be committed earlier.
The group strongly and repeatedly urged referrals for "abortion care," and states that "offering perinatal palliative care is not a substitute for providing or enabling access to abortion care."
SMFM claimed that due to "expertise and leadership positions within institutions," MFM specialists have a "unique position to uplift core tenets of reproductive justice – in particular, the ability to choose to be pregnant or not."
The Society for Maternal-Fetal Medicine (SMFM) — a membership organization founded in 1977, representing "over 6,500 members" including "Maternal-fetal medicine (MFM) subspecialist physicians" and others — has been granted over $1 million by the pro-abortion Buffett Foundation.
In 2021, the Society claimed that abortion is an "essential component of reproductive healthcare," while noting at the time that "only a small proportion of MFM physicians currently perform dilation and evacuation (D&E) procedures."
This is what a D&E abortion entails:

A 2024 position paper from the Society states that it "supports the right of all individuals to access the full spectrum of reproductive health services, including abortion care" and "opposes legislation and policies that limit access to abortion care or criminalize abortion care and self-managed abortion."
SMFM also supports the expansion of the abortion pill and the use of lethal feticides to "euthanize" — as some put it — it the preborn child in the womb.
SMFM's September 2026 statement alleges that "abortion is statistically safer than continuing a pregnancy to term," which contradicts abortionist Curtis Boyd, who claimed abortion past 18 weeks is more dangerous than childbirth.
In addition, only one study (from 2012) has shown that abortion is 14 times safer than childbirth, and those results have been unable to be replicated.
SMFM claimed that "adverse maternal outcomes" are based on "underlying medical, social, and contextual factors," revealing the fact that the group's abortion advocacy has little to do with the physical health of the mother or preborn baby.
The solution, according to SMFM, is to build "systems that can optimize care when abortion is restricted."
SMFM defines a "high-risk pregnancy" as "one that places the pregnant person, fetus, or infant at increased risk for death or residual injury and typically requires additional resources, procedures, or specialized care to optimize outcomes."
A "high-risk pregnancy," therefore, does not merely mean that an expectant mother is having health issues; it includes the idea that a child may require "specialized care" or "additional resources" once born.
These "fetal conditions that can result in a high-risk pregnancy include fetal growth restriction, fetal anomalies, and infections," says the group, adding, "These examples do not include all health conditions that might elevate risk."
Without defining the 'standard of care,' SMFM also claimed that "reproductive health services, including abortion" are necessary, but emphasized that "legal restrictions on abortion... make it challenging or impossible for clinicians to practice standard-of-care..." which frighteningly seems to imply that intentional killing is part of the job for MFM clinicians.
The obviously pro-abortion group then states "it is critical to emphasize that... MFM subspecialists," OBGYNs, and "complex family planning subspecialist colleagues are the high-risk pregnancy and abortion care experts; no other personnel are better trained to assess the risk of pregnancy complications to maternal and perinatal health."
Unfortunately, those "experts" appear to think that killing is care.
Though the group never explains how intentionally killing a preborn child falls under the "standard of care," it concludes that "Abortion care is a core component of practice for MFM subspecialists nationwide."

SMFM advocates for "earlier diagnosis of fetal anomalies" to allow "for more timely provision of abortion... especially in states with gestational duration restrictions." But early diagnosis should be a time to prepare parents, not an earlier opportunity to end a life.
Yet, SMFM claims that "All patients with a new diagnosis of a fetal anomaly should have the option of abortion care."
"Abortion care" in this context means the intentional killing or expedition of death for a child with a prenatal diagnosis.
SMFM went on to to suggest expanding "access to prenatal screening and diagnosis, including early noninvasive genetic screening and first-trimester anatomy ultrasonography" for the purpose of earlier destruction, writing that "abortion care is one of several options that should be discussed with patients in the setting of an unexpected fetal diagnosis...."
But early prenatal screening, in particular, is highly unreliable. As Live Action News previously reported, "certain prenatal genetic tests are wrong up to 93% of the time. This has major implications, given the fact that families have frequently reported experiencing pressure to abort after receiving a prenatal diagnosis for a child."
The society suggests that "Counseling regarding abortion should be included in options for pregnancy management" by "providing information and referrals about lawful abortion care," emphasizing that "offering perinatal palliative care is not a substitute for providing or enabling access to abortion care."
Horrifyingly, SMFM also writes:
Providers have an ethical obligation to discuss the mental health and health resource utilization (i.e., economic) implications of having a child with one or more health issues...
abortion care should always be discussed as a management option for any person diagnosed with a fetal congenital anomaly during pregnancy.
Furthermore, the availability of maternal-fetal surgery for a particular congenital anomaly does not preclude abortion care as an option, either at the time of diagnosis or even after maternal-fetal surgery.
SMFM also advocates for "reduction" in cases of "multifetal gestation" with "reduction," which is the intentional killing of preborn babies to reduce their number. The video below shows the targeting of a preborn twin using a potassium chloride injection:
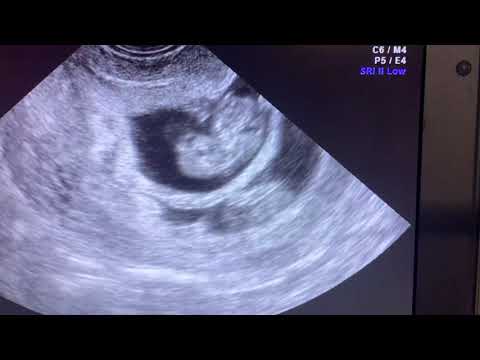
The coldness of the physician is telling:
"The needle is into the baby's heart and you can see the baby's heart beating... Once we are sure it is in the heart, we inject potassium chloride into the heart... We wait.... The heartbeat of the twin which is reduced is stopped here."
SMFM noted one of its goals is to "improve access to reproductive healthcare," encouraging clinicians to "advocate for comprehensive reproductive health counseling, inclusive of abortion care, as well as facilitation of abortion care, as an essential part of fetal care centers or fetal therapy programs.
SMFM claimed that due to "expertise and leadership positions within institutions," MFM specialists had a "unique position to uplift core tenets of reproductive justice – in particular, the ability to choose to be pregnant or not."
"Self-managed abortion (SMA)" was defined as "Steps taken to end pregnancy outside of the formal healthcare system. After SMA, patients may seek clinical care for potential complications or to confirm the abortion is complete."
SMFM also wrote of the apparent importance of "[c]ollaborative partnerships with institutions and clinics in surrounding states that provide abortion care," and called "abortion funds" an "essential resource."
The SMFM's statement was assembled by SMFM's Reproductive Health Committee and co-authored by Justin R. Lappen, who chairs the Committee.
Lappen once testified that he commits abortions "up to 21 weeks, 6 days" at the notorious Preterm abortion business in Ohio and served "as Associate Residency Program Director in Obstetrics and Gynecology and Assistant Director of a Ryan Residency Training Program in Family Planning." (Read more about Ryan Residency Programs, largely funded by billionaire abortion philanthropist Warren Buffett.)

Other authors include:
Ashish Premkumar, who pledged to provide abortions and recently disclosed that he is a consultant for the generic abortion pill manufacturer, GenBioPro.
He co-authored a paper which alleged that "exposure to abortion procedures during residency is directly linked to interest in pursuing abortion-related training in maternal-fetal medicine (MFM)," concluding that "MFM subspecialists are in a unique position to provide abortion-related reproductive care...."

Adam Crosland received a grant from a “University of California Abortion Registry (UCAR)” proposal. His LinkedIn "interests" include Planned Parenthood and Physicians for Reproductive Health.
Leilah Zahedi-Spung is also an abortionist from Tennessee who relocated to Colorado where abortion is permitted into the third trimester. She testified before a Senate hearing that "abortion is lifesaving" and "compassionate healthcare."
Given the SMFM's strong bias and argumentation in favor of abortion, families referred to maternal-fetal medicine subspecialists should be aware that the information they receive from such "experts" may trend toward death rather than real healthcare.
Live Action News is pro-life news and commentary from a pro-life perspective.
Our work is possible because of our donors. Please consider giving to further our work of changing hearts and minds on issues of life and human dignity.
Contact editor@liveaction.org for questions, corrections, or if you are seeking permission to reprint any Live Action News content.
Guest Articles: To submit a guest article to Live Action News, email editor@liveaction.org with an attached Word document of 800-1000 words. Please also attach any photos relevant to your submission if applicable. If your submission is accepted for publication, you will be notified within three weeks. Guest articles are not compensated (see our Open License Agreement). Thank you for your interest in Live Action News!
Nancy Flanders
·
Investigative
Carole Novielli
·
Investigative
Nancy Flanders
·
Investigative
Carole Novielli
·
Investigative
Bridget Sielicki
·
Investigative
Carole Novielli
·
Abortion Pill
Carole Novielli
·
Abortion Pill
Carole Novielli
·Investigative
Carole Novielli
·Investigative
Carole Novielli
·Investigative
Carole Novielli
·Investigative·By Carole Novielli
BIAS: Is the Society for Maternal-Fetal Medicine pressuring parents to abort?
The Society for Maternal-Fetal Medicine (SMFM) recently issued a statement position claiming that "Abortion... is a core component of practice for MFM subspecialists nationwide," and says practitioners are "ethically obligated" to discuss the "economic implications of having a child with one or more health issues" with families facing prenatal diagnoses.
Should families trust this pro-abortion, biased organization of subspecialists? Is this really "reproductive justice"?
The Society for Maternal-Fetal Medicine (SMFM) recently issued a statement position revealing its heavy pro-abortion bias, which stated that abortion is a "core component" of being a maternal-fetal medicine doctor.
The statement, authored by individuals involved in and/or linked to the abortion industry, also indicated that anyone receiving a prenatal diagnosis should be informed of their abortion options; not only that, but the group recommends practitioners discuss with patients the potential "economic implications" of having a child with a disability.
The group advocated for earlier diagnosis of fetal anomalies through genetic screening and testing, which is notoriously unreliable, so that abortion can be committed earlier.
The group strongly and repeatedly urged referrals for "abortion care," and states that "offering perinatal palliative care is not a substitute for providing or enabling access to abortion care."
SMFM claimed that due to "expertise and leadership positions within institutions," MFM specialists have a "unique position to uplift core tenets of reproductive justice – in particular, the ability to choose to be pregnant or not."
The Society for Maternal-Fetal Medicine (SMFM) — a membership organization founded in 1977, representing "over 6,500 members" including "Maternal-fetal medicine (MFM) subspecialist physicians" and others — has been granted over $1 million by the pro-abortion Buffett Foundation.
In 2021, the Society claimed that abortion is an "essential component of reproductive healthcare," while noting at the time that "only a small proportion of MFM physicians currently perform dilation and evacuation (D&E) procedures."
This is what a D&E abortion entails:
A 2024 position paper from the Society states that it "supports the right of all individuals to access the full spectrum of reproductive health services, including abortion care" and "opposes legislation and policies that limit access to abortion care or criminalize abortion care and self-managed abortion."
SMFM also supports the expansion of the abortion pill and the use of lethal feticides to "euthanize" — as some put it — it the preborn child in the womb.
SMFM's September 2026 statement alleges that "abortion is statistically safer than continuing a pregnancy to term," which contradicts abortionist Curtis Boyd, who claimed abortion past 18 weeks is more dangerous than childbirth.
In addition, only one study (from 2012) has shown that abortion is 14 times safer than childbirth, and those results have been unable to be replicated.
SMFM claimed that "adverse maternal outcomes" are based on "underlying medical, social, and contextual factors," revealing the fact that the group's abortion advocacy has little to do with the physical health of the mother or preborn baby.
The solution, according to SMFM, is to build "systems that can optimize care when abortion is restricted."
SMFM defines a "high-risk pregnancy" as "one that places the pregnant person, fetus, or infant at increased risk for death or residual injury and typically requires additional resources, procedures, or specialized care to optimize outcomes."
A "high-risk pregnancy," therefore, does not merely mean that an expectant mother is having health issues; it includes the idea that a child may require "specialized care" or "additional resources" once born.
These "fetal conditions that can result in a high-risk pregnancy include fetal growth restriction, fetal anomalies, and infections," says the group, adding, "These examples do not include all health conditions that might elevate risk."
Without defining the 'standard of care,' SMFM also claimed that "reproductive health services, including abortion" are necessary, but emphasized that "legal restrictions on abortion... make it challenging or impossible for clinicians to practice standard-of-care..." which frighteningly seems to imply that intentional killing is part of the job for MFM clinicians.
The obviously pro-abortion group then states "it is critical to emphasize that... MFM subspecialists," OBGYNs, and "complex family planning subspecialist colleagues are the high-risk pregnancy and abortion care experts; no other personnel are better trained to assess the risk of pregnancy complications to maternal and perinatal health."
Unfortunately, those "experts" appear to think that killing is care.
Though the group never explains how intentionally killing a preborn child falls under the "standard of care," it concludes that "Abortion care is a core component of practice for MFM subspecialists nationwide."
SMFM advocates for "earlier diagnosis of fetal anomalies" to allow "for more timely provision of abortion... especially in states with gestational duration restrictions." But early diagnosis should be a time to prepare parents, not an earlier opportunity to end a life.
Yet, SMFM claims that "All patients with a new diagnosis of a fetal anomaly should have the option of abortion care."
"Abortion care" in this context means the intentional killing or expedition of death for a child with a prenatal diagnosis.
SMFM went on to to suggest expanding "access to prenatal screening and diagnosis, including early noninvasive genetic screening and first-trimester anatomy ultrasonography" for the purpose of earlier destruction, writing that "abortion care is one of several options that should be discussed with patients in the setting of an unexpected fetal diagnosis...."
But early prenatal screening, in particular, is highly unreliable. As Live Action News previously reported, "certain prenatal genetic tests are wrong up to 93% of the time. This has major implications, given the fact that families have frequently reported experiencing pressure to abort after receiving a prenatal diagnosis for a child."
The society suggests that "Counseling regarding abortion should be included in options for pregnancy management" by "providing information and referrals about lawful abortion care," emphasizing that "offering perinatal palliative care is not a substitute for providing or enabling access to abortion care."
Horrifyingly, SMFM also writes:
Providers have an ethical obligation to discuss the mental health and health resource utilization (i.e., economic) implications of having a child with one or more health issues...
abortion care should always be discussed as a management option for any person diagnosed with a fetal congenital anomaly during pregnancy.
Furthermore, the availability of maternal-fetal surgery for a particular congenital anomaly does not preclude abortion care as an option, either at the time of diagnosis or even after maternal-fetal surgery.
SMFM also advocates for "reduction" in cases of "multifetal gestation" with "reduction," which is the intentional killing of preborn babies to reduce their number. The video below shows the targeting of a preborn twin using a potassium chloride injection:
The coldness of the physician is telling:
"The needle is into the baby's heart and you can see the baby's heart beating... Once we are sure it is in the heart, we inject potassium chloride into the heart... We wait.... The heartbeat of the twin which is reduced is stopped here."
SMFM noted one of its goals is to "improve access to reproductive healthcare," encouraging clinicians to "advocate for comprehensive reproductive health counseling, inclusive of abortion care, as well as facilitation of abortion care, as an essential part of fetal care centers or fetal therapy programs.
SMFM claimed that due to "expertise and leadership positions within institutions," MFM specialists had a "unique position to uplift core tenets of reproductive justice – in particular, the ability to choose to be pregnant or not."
"Self-managed abortion (SMA)" was defined as "Steps taken to end pregnancy outside of the formal healthcare system. After SMA, patients may seek clinical care for potential complications or to confirm the abortion is complete."
SMFM also wrote of the apparent importance of "[c]ollaborative partnerships with institutions and clinics in surrounding states that provide abortion care," and called "abortion funds" an "essential resource."
The SMFM's statement was assembled by SMFM's Reproductive Health Committee and co-authored by Justin R. Lappen, who chairs the Committee.
Lappen once testified that he commits abortions "up to 21 weeks, 6 days" at the notorious Preterm abortion business in Ohio and served "as Associate Residency Program Director in Obstetrics and Gynecology and Assistant Director of a Ryan Residency Training Program in Family Planning." (Read more about Ryan Residency Programs, largely funded by billionaire abortion philanthropist Warren Buffett.)
Other authors include:
Ashish Premkumar, who pledged to provide abortions and recently disclosed that he is a consultant for the generic abortion pill manufacturer, GenBioPro.
He co-authored a paper which alleged that "exposure to abortion procedures during residency is directly linked to interest in pursuing abortion-related training in maternal-fetal medicine (MFM)," concluding that "MFM subspecialists are in a unique position to provide abortion-related reproductive care...."
Adam Crosland received a grant from a “University of California Abortion Registry (UCAR)” proposal. His LinkedIn "interests" include Planned Parenthood and Physicians for Reproductive Health.
Leilah Zahedi-Spung is also an abortionist from Tennessee who relocated to Colorado where abortion is permitted into the third trimester. She testified before a Senate hearing that "abortion is lifesaving" and "compassionate healthcare."
Given the SMFM's strong bias and argumentation in favor of abortion, families referred to maternal-fetal medicine subspecialists should be aware that the information they receive from such "experts" may trend toward death rather than real healthcare.
Live Action News is pro-life news and commentary from a pro-life perspective.
Our work is possible because of our donors. Please consider giving to further our work of changing hearts and minds on issues of life and human dignity.
Contact editor@liveaction.org for questions, corrections, or if you are seeking permission to reprint any Live Action News content.
Guest Articles: To submit a guest article to Live Action News, email editor@liveaction.org with an attached Word document of 800-1000 words. Please also attach any photos relevant to your submission if applicable. If your submission is accepted for publication, you will be notified within three weeks. Guest articles are not compensated (see our Open License Agreement). Thank you for your interest in Live Action News!
Nancy Flanders
·Investigative
Carole Novielli
·Investigative
Nancy Flanders
·Investigative
Carole Novielli
·Investigative
Bridget Sielicki
·Investigative
Carole Novielli
·Abortion Pill
Carole Novielli
·Abortion Pill
Carole Novielli
·Investigative
Carole Novielli
·Investigative
Carole Novielli
·Investigative
Carole Novielli
·